Introduction: why a framework matters
Delivering robust immunology trials requires a repeatable structure that aligns scientific rigour with operational clarity. This framework begins with preclinical validation using recognised resources such as autoimmune disease models, then moves through assay design, site selection and staged data review. Practical choices at each step reduce variability and speed reliable readouts; murine baseline work often determines assay feasibility and translational value. A Real-World Anchor: many Indian research centres, including groups at the Indian Institute of Science in Bangalore, documented rapid optimisation of murine models during the 2020–2021 response to acute inflammatory challenges, reinforcing the need for early, reproducible model selection.
Framework step 1 — Define trial objectives and translational endpoints
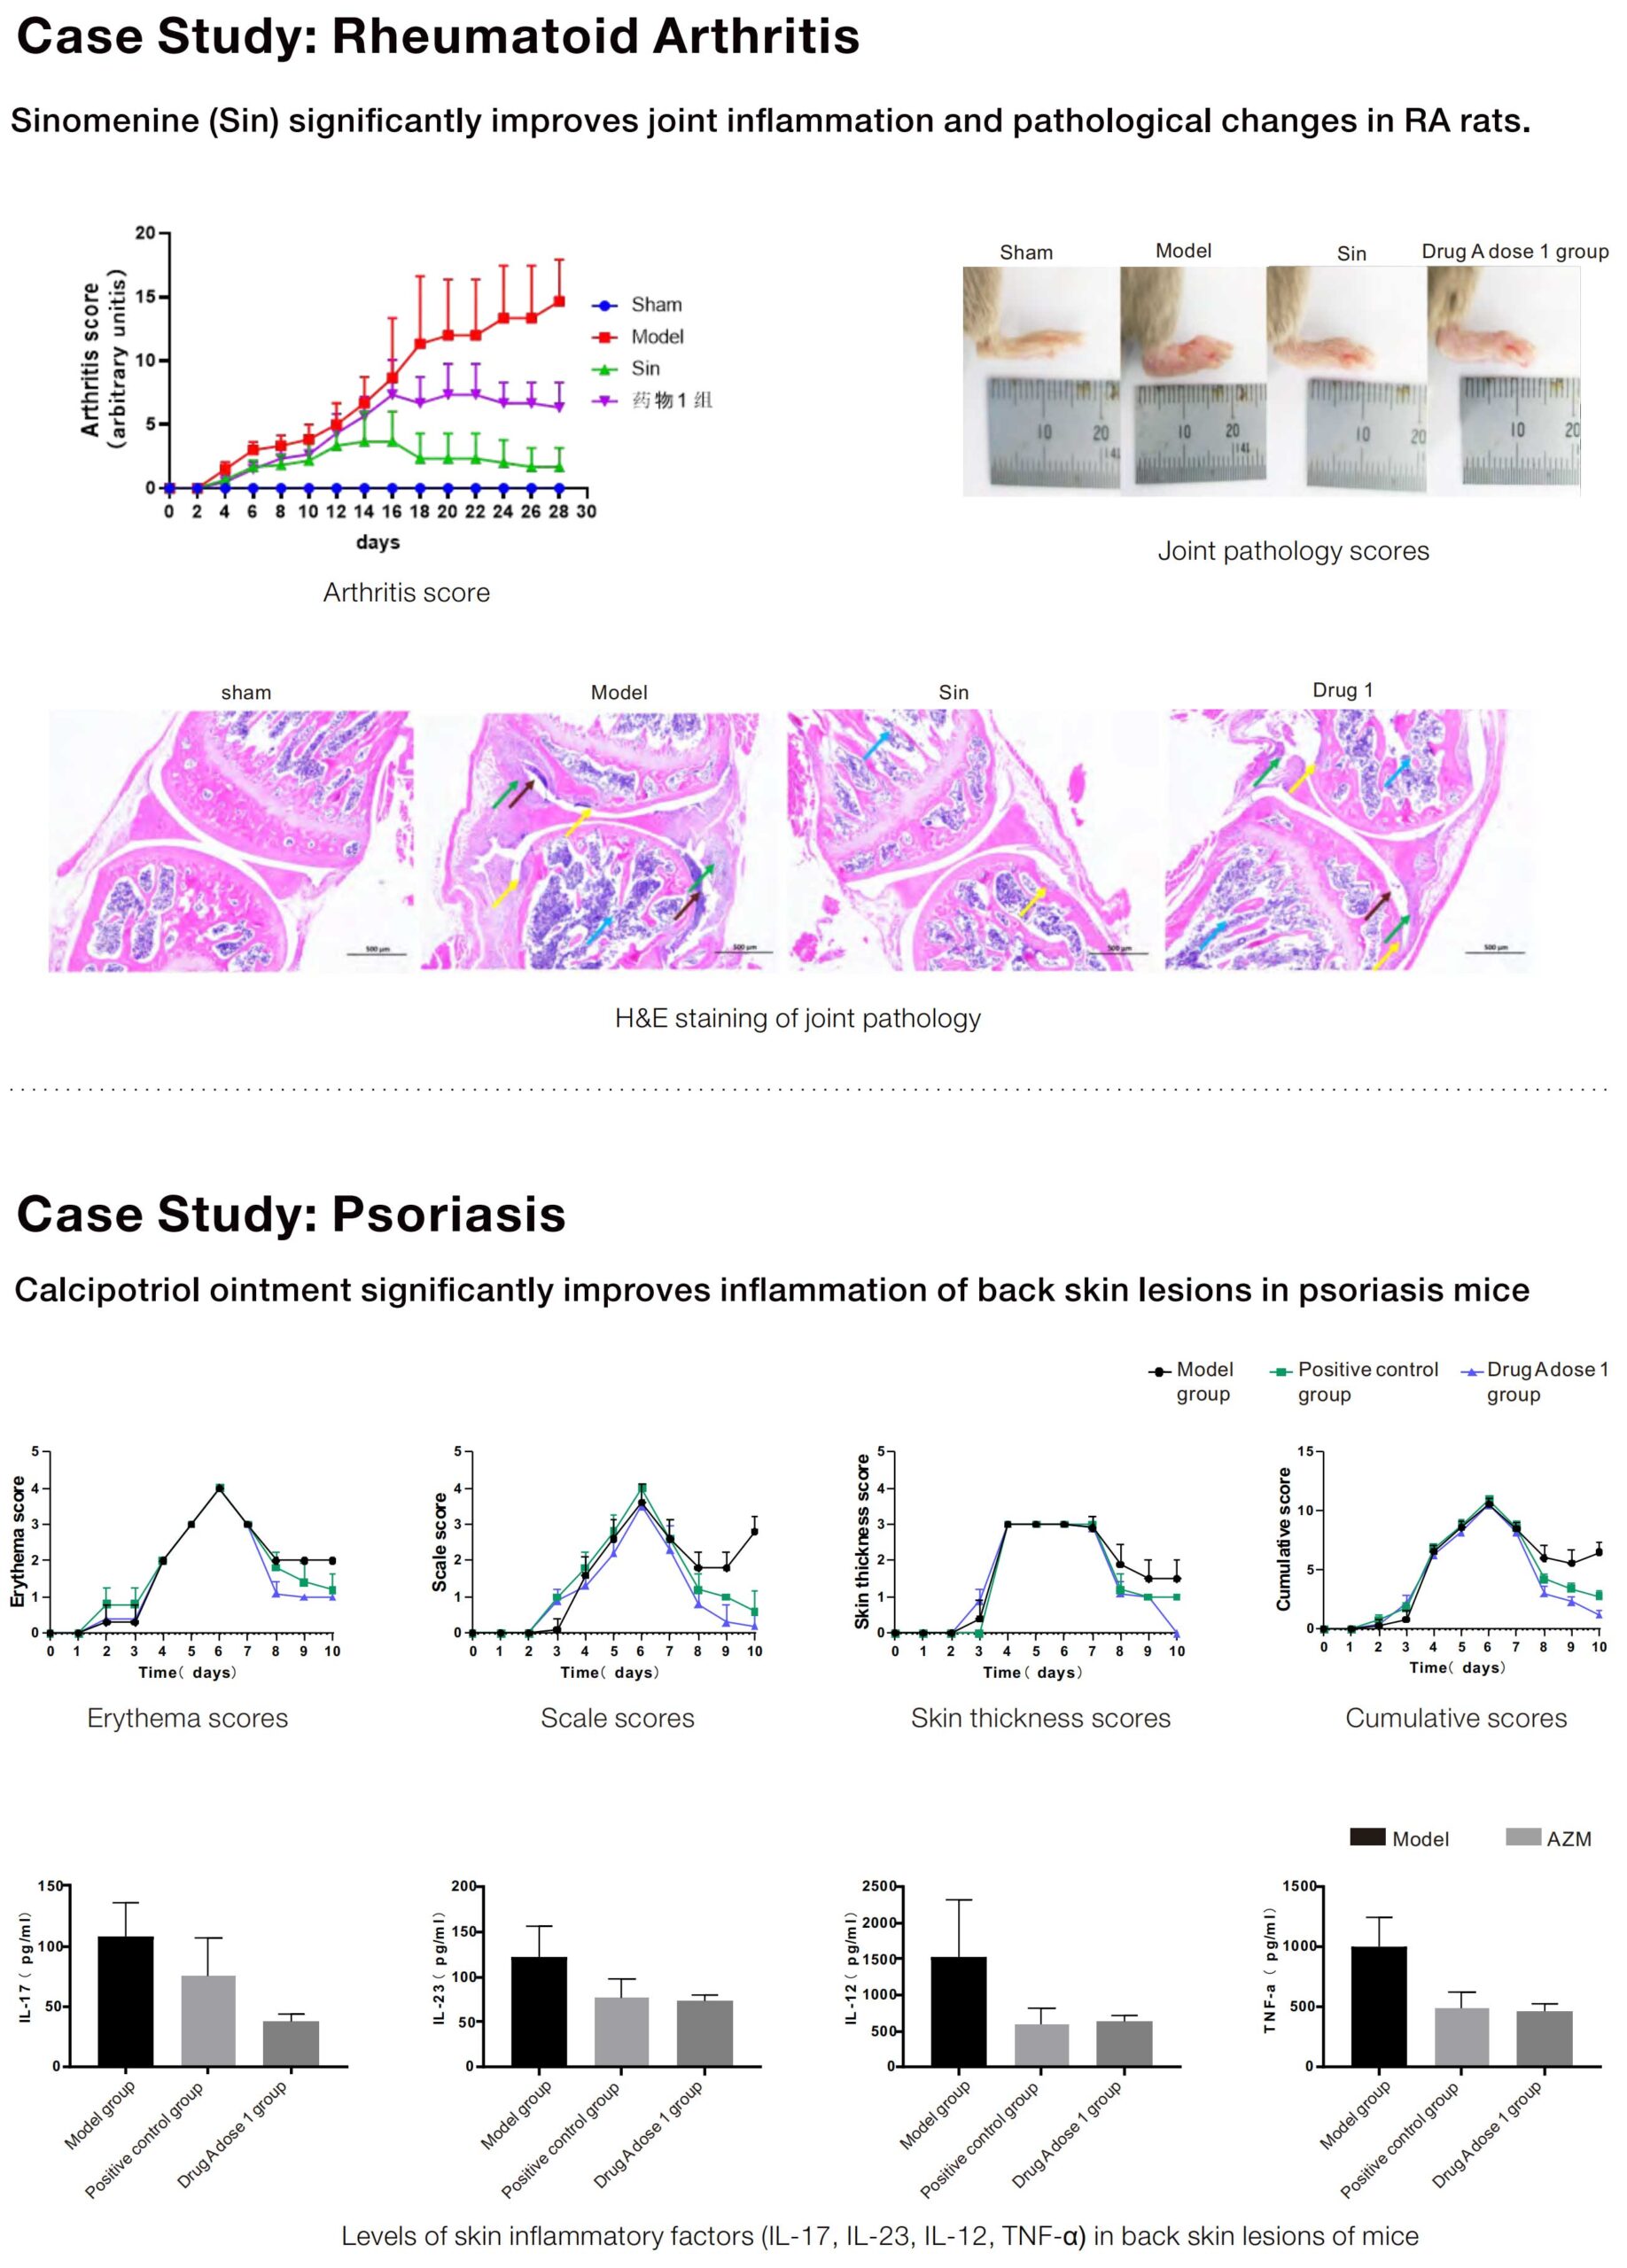
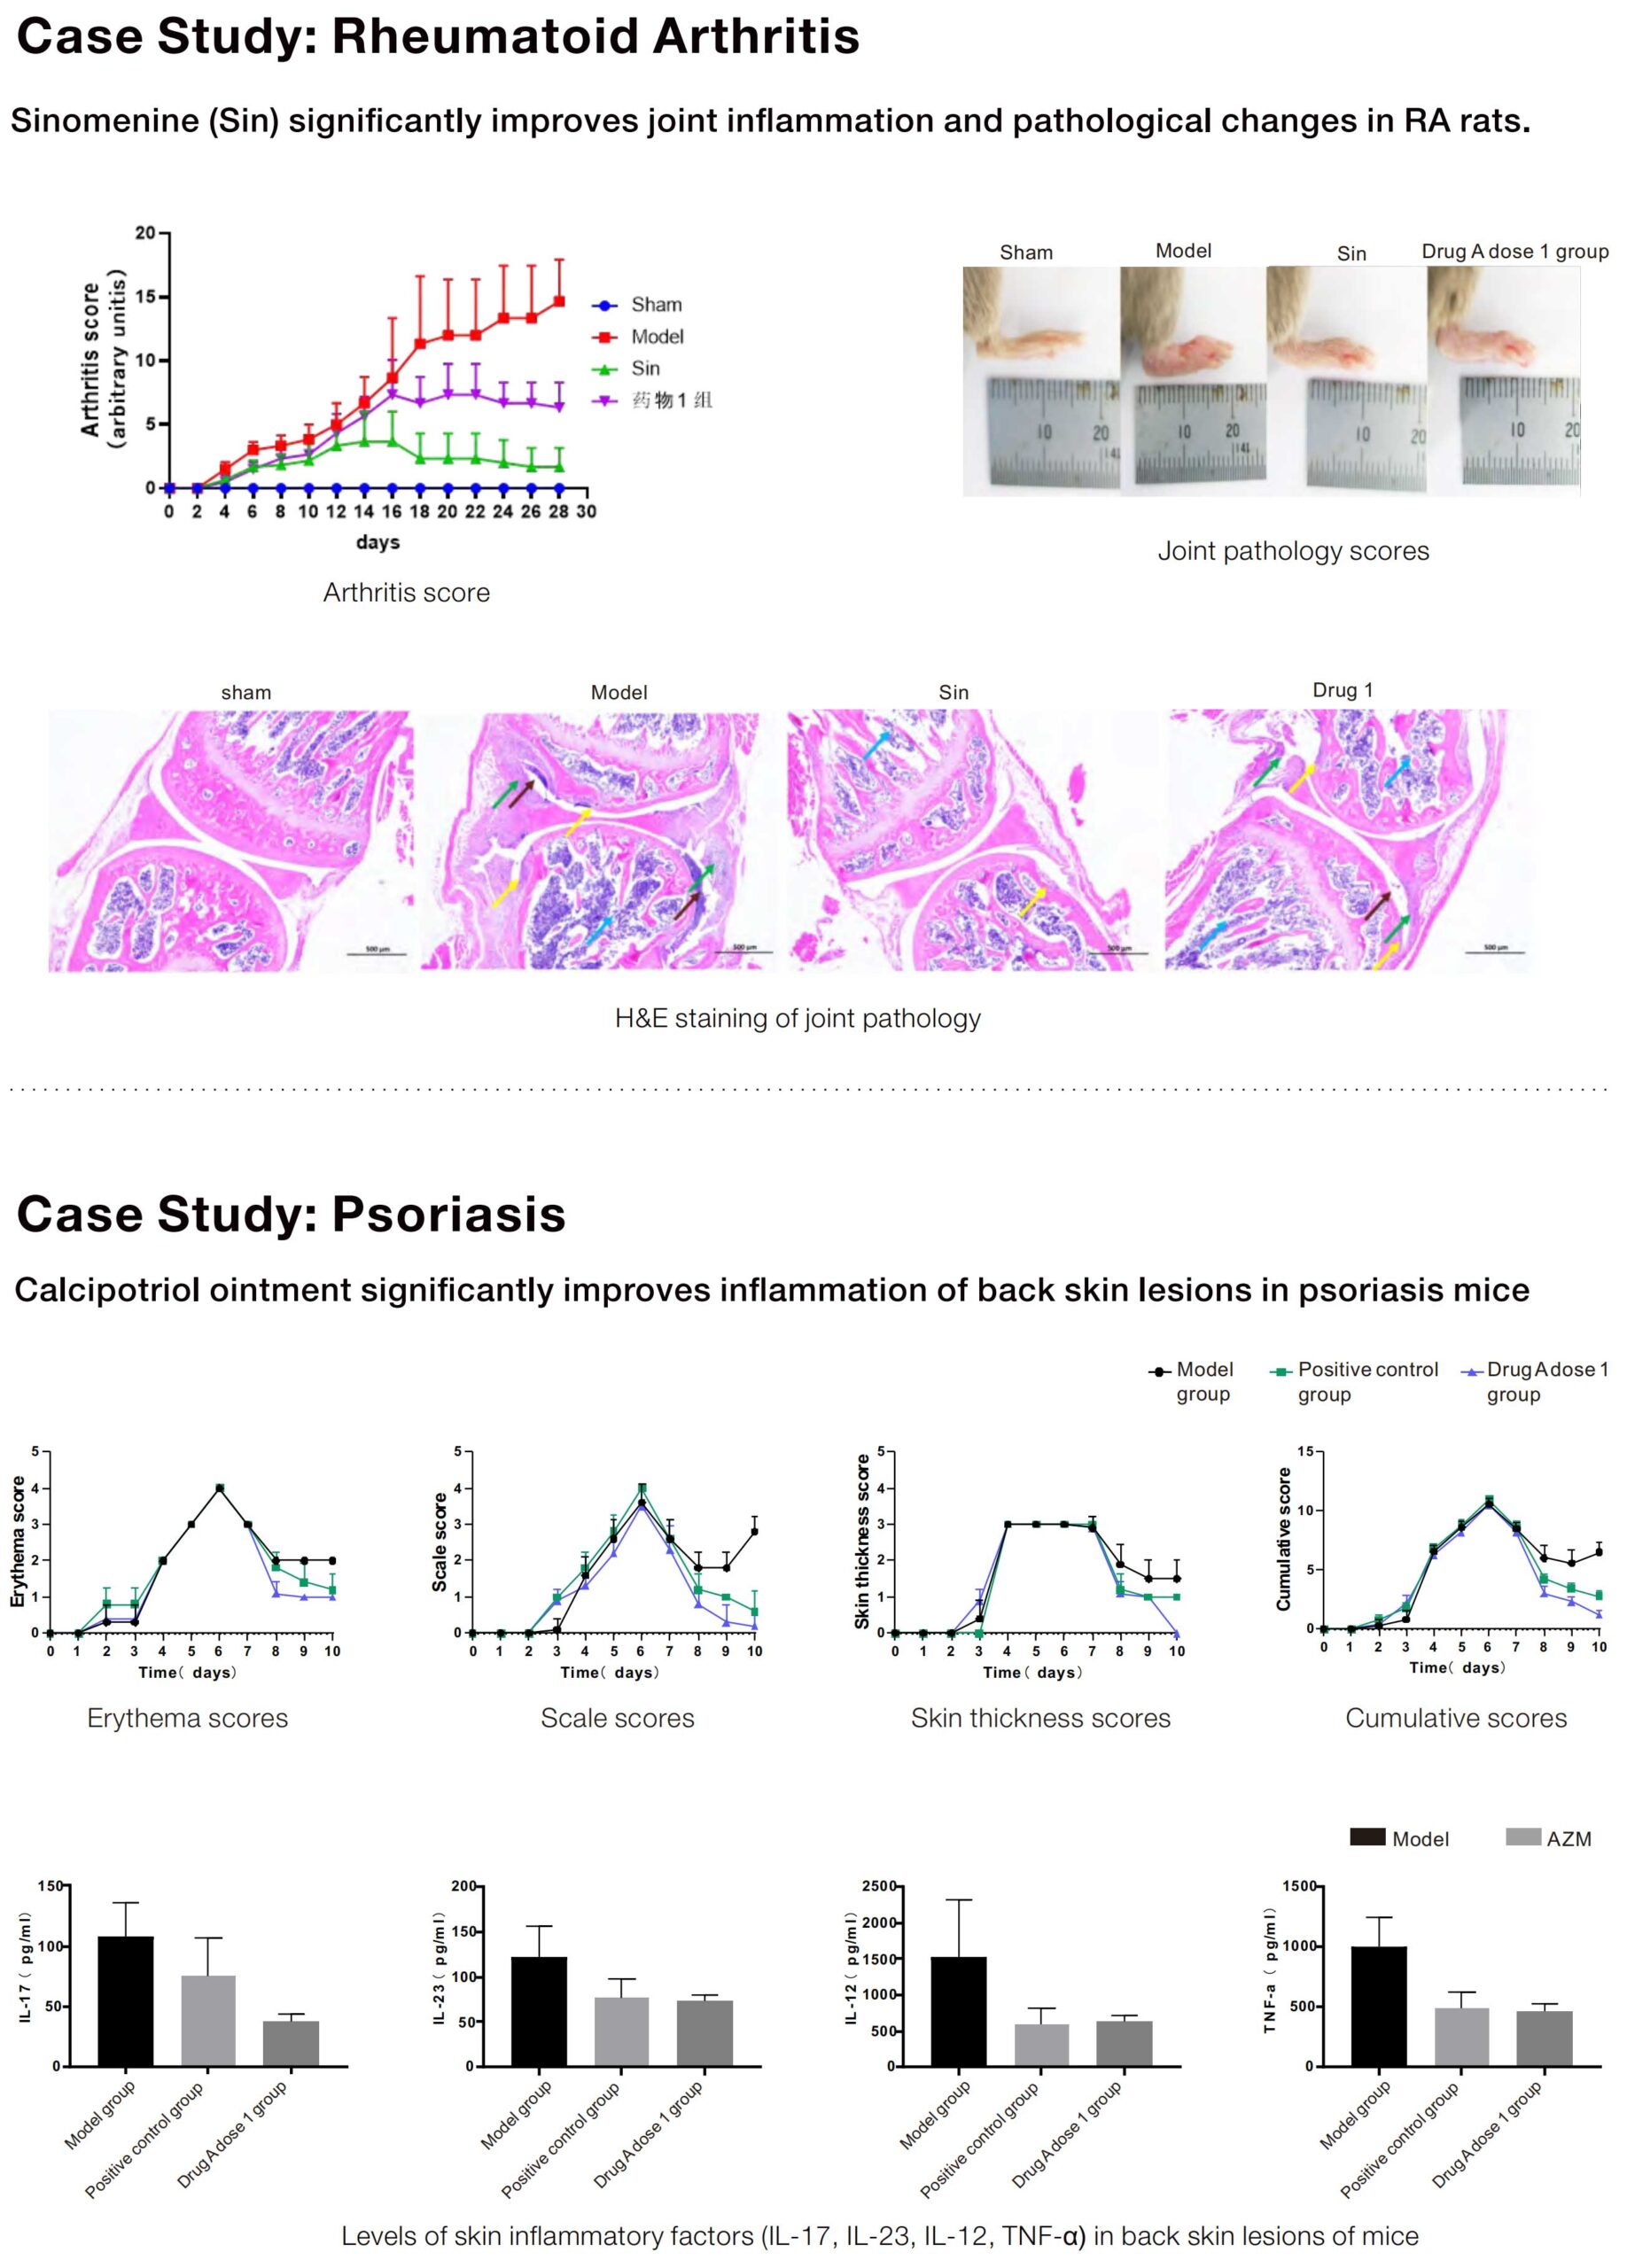
Begin by converting clinical hypotheses into measurable preclinical and clinical endpoints. Use clear endpoints such as cytokine profiling, clinical scoring systems for arthritis models, or histopathology grades that map onto regulatory expectations. Specify the operational production teardown: align sample timepoints, assay sensitivity, and statistical power calculations. In that teardown, balance {main_keyword} with {variation_keyword} when choosing biomarker panels to avoid downstream rework.
Framework step 2 — Model selection and validation
Choose models that predict human biology with demonstrated face and construct validity. Common options include collagen-induced arthritis and adjuvant-induced arthritis for rheumatoid-like phenotypes, alongside genetically engineered murine models for mechanistic insight. Validate with pilot cohorts and blinded readouts before scaling; confirm reproducibility across technicians, batches and cages. Early investment in proper control groups and consistent husbandry pays off—small lapses here produce noisy datasets later.
Framework step 3 — Assays, QC and data flow
Design assays that survive real-world variability. Standard operating procedures should cover sample collection windows, assay calibration, and acceptance criteria for inter-assay coefficient of variation. Use multiplex cytokine panels cautiously—cross-reactivity and matrix effects require pre-study validation. Implement a centralised data pipeline with versioned metadata to ensure traceability from raw files to analysed endpoints. Incorporate inflammation models in mice into assay validation plans where possible to demonstrate translational signal prior to clinical moves.
Common mistakes and practical mitigations
Teams typically repeat a handful of avoidable errors: underpowered pilots, heterogeneous control groups, and poorly defined stopping rules. Mitigations are straightforward—standardise animal sourcing, use blinded scoring, and pre-register statistical plans. A mid-project technical pause for a quality audit reduces costly repeats. Attention to housing, diet and light cycles often resolves otherwise mysterious variability—these are mundane factors but decisive in outcome quality.
Comparative choices: in-house versus CRO partners
Deciding between in-house capabilities and contract research organisations depends on throughput needs and technical depth. In-house work gives tight control over models and rapid iteration; CROs offer scale, GLP infrastructure and multi-site harmonisation. A hybrid approach often works best: validate core mechanistic endpoints internally, then transfer validated assays to CROs for larger, blinded studies. Keep transition checklists for assay acceptance criteria and sample logistics to avoid drift during handover.
Advisory: three golden rules for evaluation
1) Reproducibility first — demand blinded replicate runs and report inter-run variability as a non-negotiable metric. 2) Translational alignment — prioritise models and biomarkers with established correlation to clinical outcomes (for example, cytokine signatures or histopathology grades known to predict therapeutic response). 3) Operational readiness — ensure sample handling, cold chain and data pipelines meet predefined tolerances before scaling. These rules let teams judge partners and platforms objectively and consistently.
Closing reflection
Implementing this framework yields clearer decision points, fewer reruns and stronger translational confidence—metrics that matter when moving from bench to bedside. Jennio Biotech sits naturally in this chain, offering validated inflammation and autoimmune resources that dovetail with the operational checks above; the brand’s models often shorten the validation curve. Final thought — practical, tested systems beat speculation every time. —