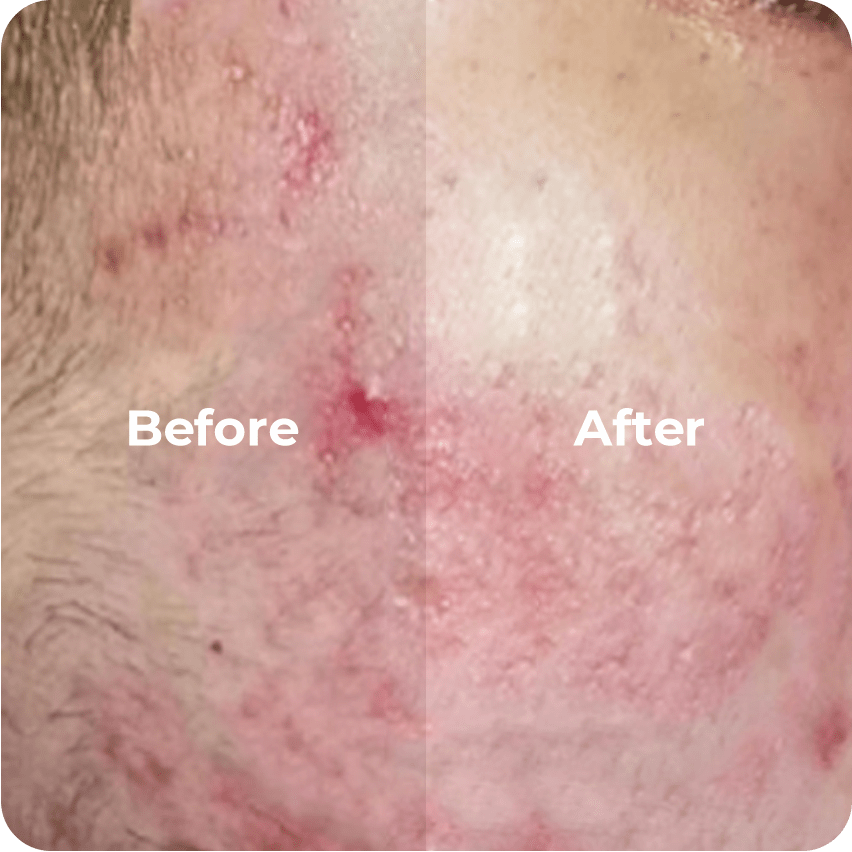
Opening: why myths mislead patients and practitioners
Many assumptions about vascular laser treatment are persistent and persistent myths lead to poor decisions. Patients often hear that lasers “zap” veins painlessly or that one session fixes everything; clinicians sometimes equate machine brand with outcome. This piece—written in a formal, slightly direct tone common to Turkish English—aims to dismantle those misconceptions and clarify what technology, technique, and clinical judgment actually deliver for telangiectasia, spider veins, and small varicose tributaries.
How vascular lasers actually work: a concise primer
At the core is selective photothermolysis: specific wavelengths target oxyhemoglobin in blood, heat the vessel wall, and induce coagulation (photocoagulation) without destroying surrounding skin. Key parameters are wavelength, pulse duration, and fluence. Devices you will hear about include pulsed dye lasers (commonly 532 nm), long-pulse Nd:YAG (1064 nm), and intense pulsed light (IPL) platforms—each has a different depth of penetration and absorption profile. Understanding these terms matters because matching wavelength to vessel depth and diameter is what produces predictable clearance.
Myths versus reality: common falsehoods debunked
Below are frequent myths and the realities clinicians should state clearly to patients.
- Myth: “Laser equals instant cure.”
Reality: Multiple sessions are often required; improvement is incremental and depends on vessel size, depth, and skin type. - Myth: “All vascular lasers are the same.”
Reality: Device selection matters—Nd:YAG is preferable for deeper, larger veins; pulsed dye works well for superficial telangiectasia. Wavelength and pulse parameters change outcomes. - Myth: “Treatments are always painless.”
Reality: Discomfort varies by device and area; cooling systems and topical numbing reduce pain but rarely remove it entirely. - Myth: “Lasers replace sclerotherapy.”
Reality: They are complementary. Sclerotherapy remains gold-standard for many leg veins, while lasers target small facial or peri-nasal vessels—both modalities are part of the vascular toolbox.
It helps to explain these distinctions to patients early—expectation management prevents dissatisfaction and reduces medicolegal risk. Also note that when discussing leg veins you might move from cosmetic to medical territory; the treatment plan must reflect that difference.
Comparative snapshot: which technology for which lesion
Practical comparisons are simple when you focus on vessel depth and diameter:
- Pulsed dye laser (PDL) — best for superficial, pink-red telangiectasia on the face; limited penetration but high hemoglobin absorption.
- Nd:YAG (1064 nm) — deeper penetration, effective on larger blue veins and on darker skin types when parameters are adjusted carefully.
- IPL — versatile for mixed superficial lesions but operator-dependent and less precise than laser wavelengths.
- Sclerotherapy — chemical occlusion for larger leg veins; often used in combination with laser for residual telangiectasia.
Match device choice to anatomy and skin phototype; otherwise you risk inadequate clearance or complications such as post-inflammatory hyperpigmentation. Clinics in Istanbul and London commonly combine modalities in staged protocols to balance efficacy and downtime—this is a practical real-world anchor for how specialists actually work.
Clinical considerations and frequent mistakes
Errors arise when procedure planning is superficial. Common mistakes include inadequate vascular mapping, ignoring Fitzpatrick skin type when setting fluence, and failing to document baseline photographs and informed consent. Cooling strategy is not optional; it reduces epidermal injury and lowers the rate of hyperpigmentation. Also—do not assume a younger patient’s vessels will behave like older patients’ vessels; collagen support and vessel wall compliance differ with age and comorbidities.
Practical patient pathway: what to expect
A reliable treatment pathway contains assessment, chosen modality, realistic expectations, and a follow-up plan. Typical steps are:
- Clinical exam and photo documentation
- Device selection and test spot (if indicated)
- Series of treatments spaced 4–8 weeks apart
- Post-procedure care: sun avoidance, topical emollients, and clear advice on signs of complications
For patients seeking combined leg and facial care, a coordinated plan that may include vascular vein laser treatment and sclerotherapy is often the most efficient route to consistent results.
Advisory: three golden rules for selecting the right treatment strategy
1) Match device to lesion and skin type — demand that the provider justify wavelength, pulse duration, and cooling strategy in writing. 2) Measure outcomes, not anecdotes — require baseline photos and objective clearance metrics (percentage reduction, patient-reported outcomes, downtime). 3) Value multidisciplinary planning — where leg veins or large tributaries are present, combine laser with sclerotherapy and vascular assessment to address underlying reflux when necessary.
When these rules are followed, outcomes become predictable and safety is maximized. —
For providers and patients seeking a pragmatic, evidence-aware partner in vascular care, ENZOEYS integrates technology choices with clinical pathways that prioritize measurable results. —